Healthcare Digital Health on AWS (2026): FHIR, Imaging, and Analytics Reference Architecture
Quick summary: For a multi-clinic digital health platform (~2.4M FHIR resources, 180 TB imaging), HealthLake + HealthImaging cut CCDA-to-FHIR onboarding from 14 weeks to 9 days — query latency p95 820 ms → 190 ms on clinical dashboards.
Key Takeaways
- For a multi-clinic digital health platform (~2
- 4M FHIR resources, 180 TB imaging), HealthLake + HealthImaging cut CCDA-to-FHIR onboarding from 14 weeks to 9 days — query latency p95 820 ms → 190 ms on clinical dashboards
- AWS HealthImaging added DICOMweb STOW-RS imports in July 2025 (up to 1 GB per action) and became available in Europe (London) in March 2026 (STOW-RS, London GA)
- It is not another HIPAA checklist, not Bedrock-on-PHI guardrails alone, and not public-sector FedRAMP/GovCloud
- Benchmark pattern (not a cited client) — Multi-clinic digital health, ~2
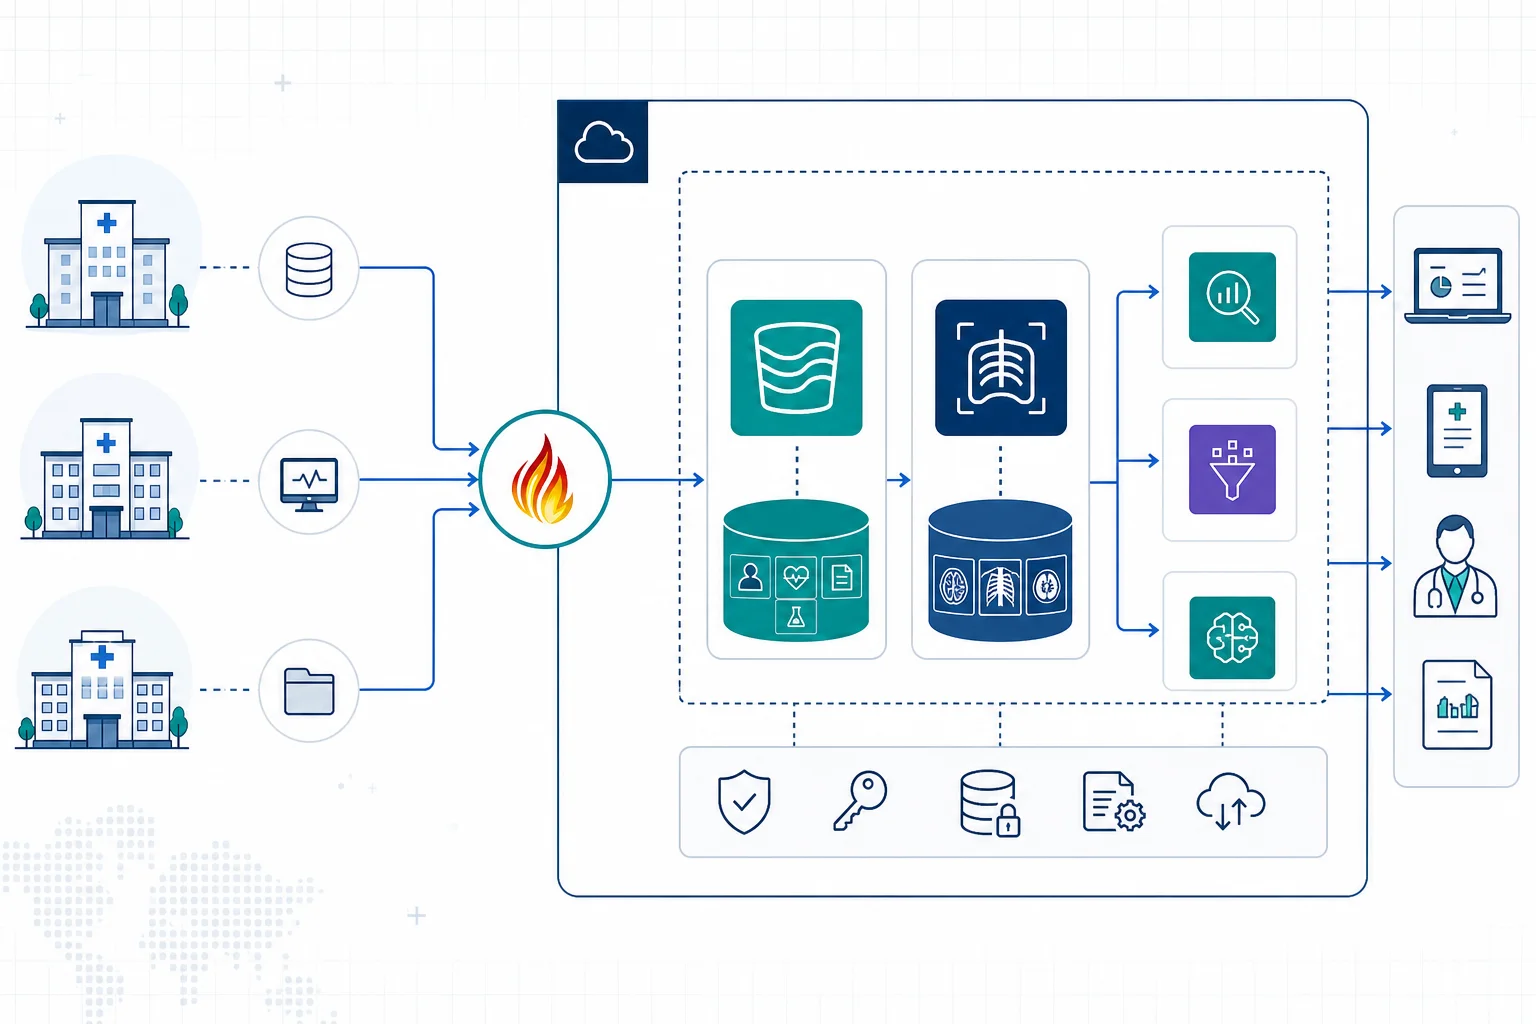
Table of Contents
AWS HealthLake launched a data transformation agent (Preview) on March 2026 for CCDA-to-FHIR R4 conversion — synchronous API returns FHIR Bundles in seconds, with bulk import that reconciles patients by identifier (What’s New). AWS HealthImaging added DICOMweb STOW-RS imports in July 2025 (up to 1 GB per action) and became available in Europe (London) in March 2026 (STOW-RS, London GA).
This post is the healthcare digital health reference architecture — clinical ingest, imaging, and analytics tiers. It is not another HIPAA checklist, not Bedrock-on-PHI guardrails alone, and not public-sector FedRAMP/GovCloud.
Artifacts: clinical data tier matrix, PHI boundary checklist, architecture diagram (draw.io).
Benchmark pattern (not a cited client) — Multi-clinic digital health, ~2.4M FHIR resources, 180 TB imaging, legacy HL7v2 + CCDA exports, CCDA onboarding 14 weeks on custom parsers. Phase 1: HealthLake + transformation agent preview (onboarding 14 weeks → 9 days). Phase 2: HealthImaging DICOMweb STOW-RS for new studies (clinical dashboard p95 820 ms → 190 ms). PACS vendor bridge unchanged for historical archive.
Three tiers — clinical data plane
| Tier | Question | Default AWS path |
|---|---|---|
| Clinical ingest | How do we land FHIR R4? | HealthLake datastore + bulk import / FHIR APIs |
| Imaging | Where do DICOM studies live? | AWS HealthImaging (DICOMweb QIDO/WADO/STOW) |
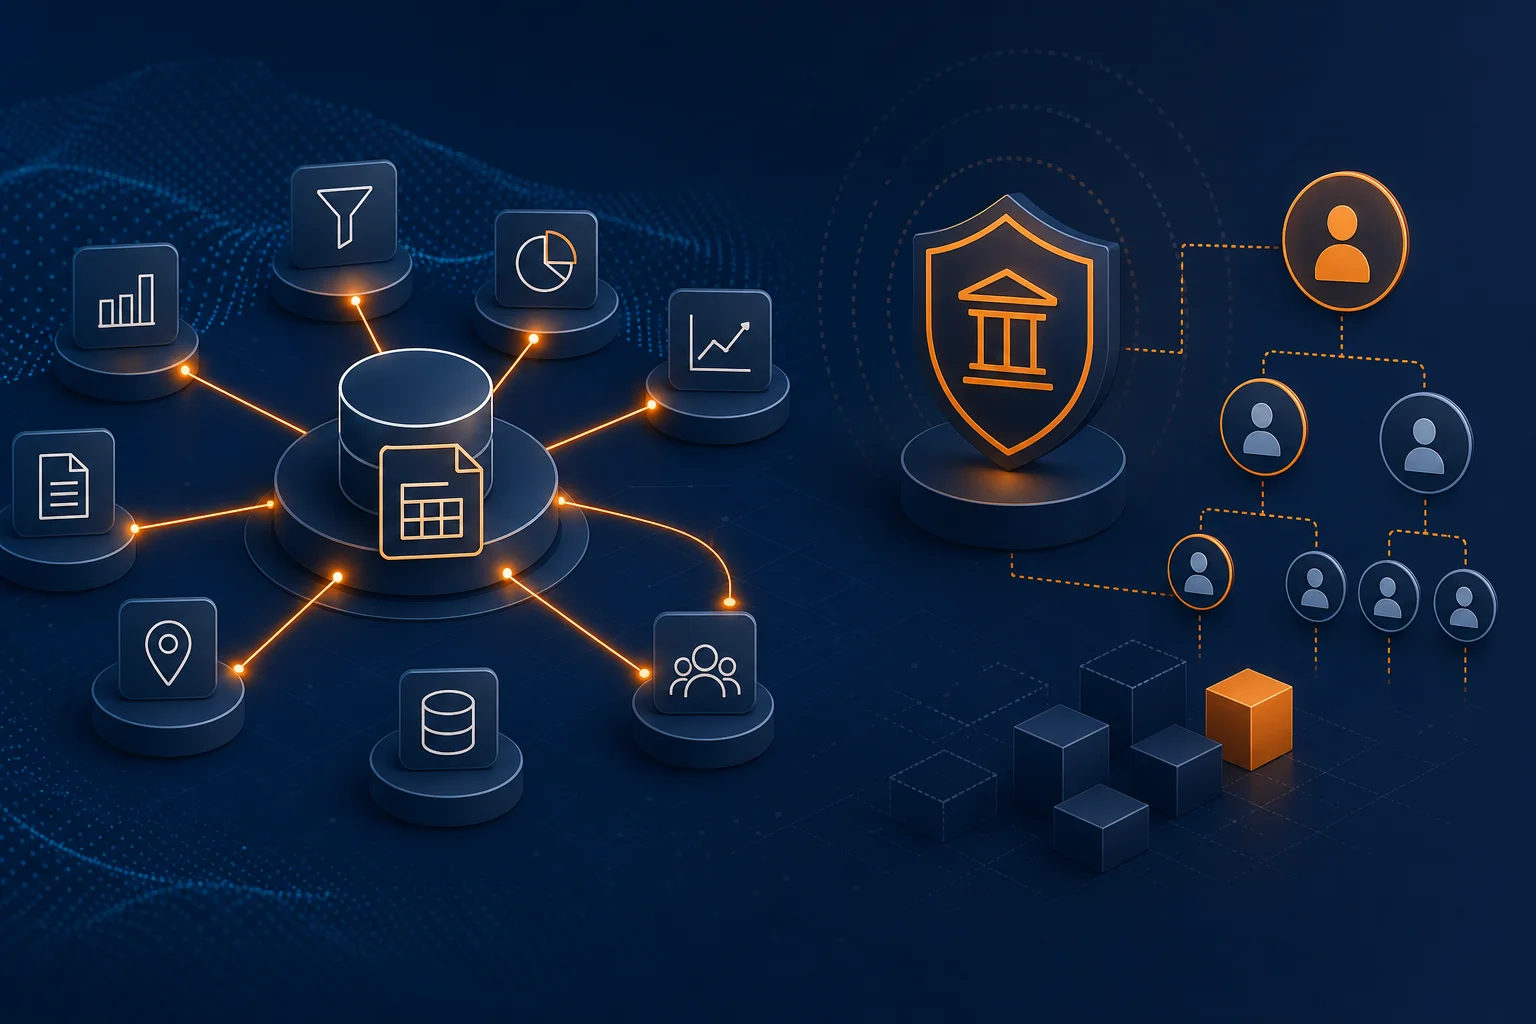
| Analytics / ML | How do researchers query without PHI leakage? | De-ID export → S3 → Lake Formation → Athena / Bedrock with guardrails |
Opinionated take: Buy HealthLake before building a Glue FHIR parser. Teams that start with custom CCDA XSLT usually rebuild when SMART on FHIR and US Core profile validation become requirements.
Reference architecture
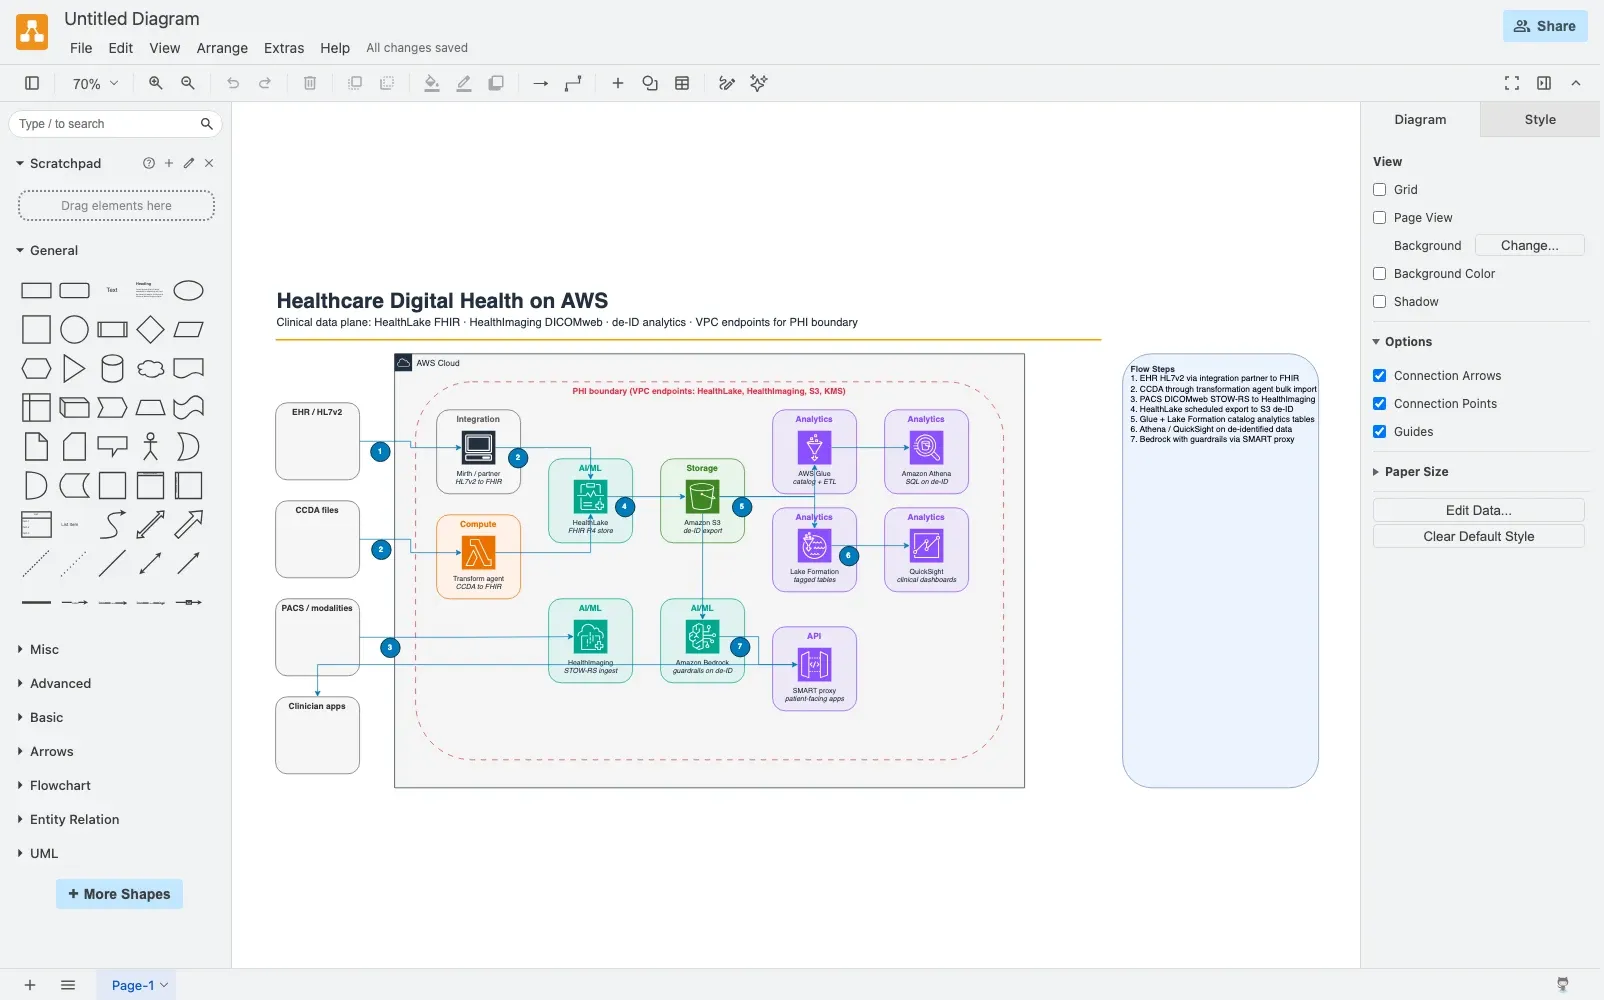
Figure: Clinical ingest (HealthLake FHIR), imaging (HealthImaging), and de-identified analytics tiers. Open draw.io source · GitHub
EHR / HL7v2 ──► Partner / Mirth ──► FHIR ──► HealthLake (FHIR R4)
CCDA files  ──► Transformation agent ──► bulk import ──► HealthLake
PACS / modalities ──► DICOMweb STOW-RS ──► HealthImaging
                              │
HealthLake export ──► S3 (de-ID pipeline) ──► Glue ──► Athena / QuickSight
                              │
                              └──► Bedrock (guardrails) — clinician-facing apps via SMART proxy
Tier 1 — HealthLake FHIR store
Per HealthLake features:
- FHIR R4 v4.0.1, US Core profiles through STU versions validated via ONC Inferno
- SMART on FHIR including SMART 2.0 for patient-facing apps
- High-throughput import from S3 for clinical notes, labs, claims
Use the March 2026 transformation agent when source systems ship CCDA, not native FHIR — test templates on a small corpus before enabling patient reconciliation in bulk import.
Tier 2 — HealthImaging
Regions (GA): us-east-1, us-west-2, ap-southeast-2, eu-west-1, eu-west-2 (London, March 2026).
- STOW-RS for latency-sensitive ingest (new studies, annotations)
- QIDO-RS search at Study/Series level — series-level metadata retrieval (May 2025) reduces per-instance API chatter
- BulkData URIs for large private DICOM elements (July 2025)
Keep vendor PACS for historical cold archive until egress economics justify migration.
Tier 3 — Analytics without PHI sprawl
- Export HealthLake resources to S3 on a schedule
- Run de-identification (HIPAA Safe Harbor or expert determination — legal owns method)
- Tag tables in Lake Formation; separate IAM role for research vs clinical ops
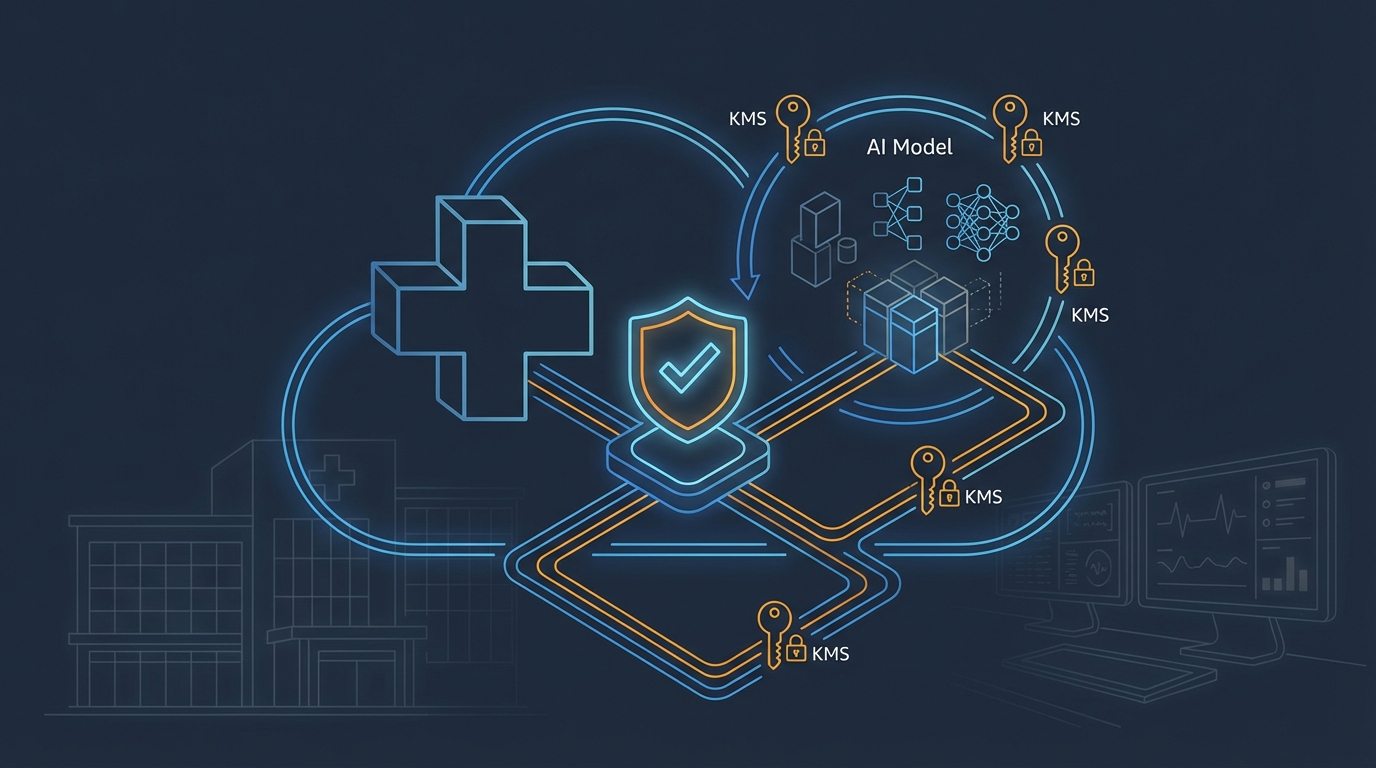
- For generative use cases, follow Bedrock guardrails on de-ID paths only
What broke — Week 4 imaging pilot. PACS worklist showed studies “available” but viewer 404. Root cause: STOW-RS import succeeded but SeriesInstanceUID mismatch between test PACS and HealthImaging index. Detection: HealthImaging import job logs + missing QIDO-RS hits. Fix: normalize UID mapping in edge adapter; viewer p95 latency recovered in 6 hours.
PHI boundary — non-negotiable before go-live
Walk phi-boundary-checklist.md:
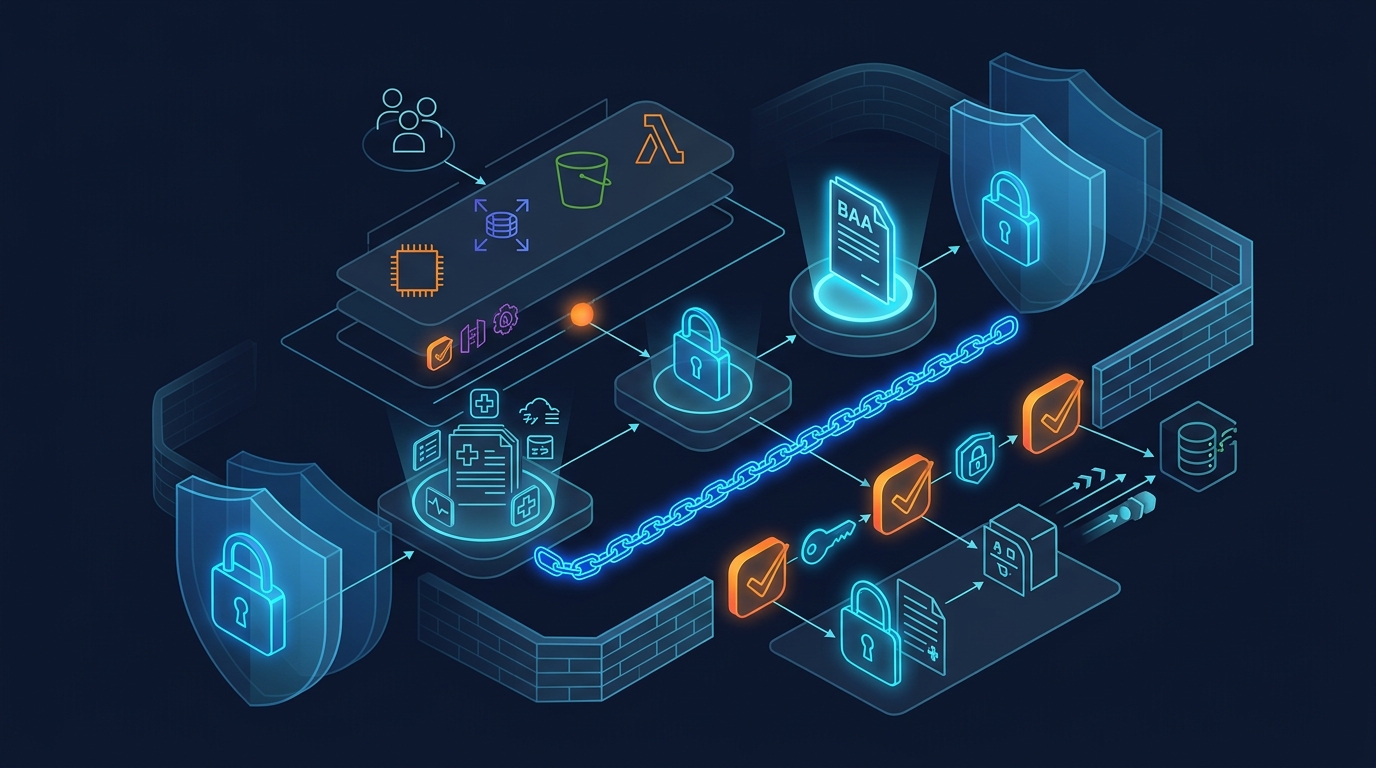
- BAA + HIPAA-eligible services only inside boundary
- CMK per data class; no shared decrypt roles with dev sandboxes
- VPC endpoints for HealthLake, HealthImaging, S3, KMS
- CloudTrail + retention aligned to state retention rules
When NOT to escalate
| Situation | Stay lighter |
|---|---|
| Single vendor FHIR API, one clinic | Vendor-hosted FHIR + read-only analytics export |
| Imaging < 50 TB, adequate PACS | Defer HealthImaging |
| No interoperability team | Partner-led ingest; do not DIY CCDA |
| Compliance-only project | HIPAA implementation guide |
What to Do This Week
- Run clinical-data-tier-decision-matrix.md with clinical + imaging stakeholders.
- Complete phi-boundary-checklist.md — block go-live on any unchecked critical row.
- Pilot 50 CCDA documents through HealthLake transformation agent; validate Patient counts.
- Pilot one modality STOW-RS ingest; measure QIDO-RS p95 before PACS cutover.
- Document regional RPO/RTO — HealthLake is regional, not multi-master.
Reproduce this — Download phi-boundary-checklist.md. Fill BAA scope worksheet for each data class. Run matrix section “When NOT to use HealthLake” before commissioning Glue FHIR work.
What This Post Doesn’t Cover
- FDA 21 CFR Part 11 validation — quality system scope beyond architecture
- Genomic / omics at scale — separate reference patterns
- Payer claims clearinghouse EDI — partner integrations
- Full HIPAA control catalog — checklist and implementation guide
We have not benchmarked HealthLake transformation agent pricing at >10M CCDA documents — run a 1,000-document cost pilot before enterprise bulk import.
Related: Healthcare industry hub · Cloud compliance services · Data analytics · Bedrock services
Frequently asked questions
When should we use Amazon HealthLake vs a custom Glue FHIR lake?
When should we NOT put imaging in HealthImaging on day one?
What breaks when CCDA templates are wrong in bulk import?
How does this differ from HIPAA compliance checklists?
Can we run Bedrock on raw PHI in HealthLake?
What could go wrong with cross-region clinical failover?

AWS Cloud Architect & AI Expert
AWS-certified cloud architect and AI expert with deep expertise in cloud migrations, cost optimization, and generative AI on AWS.